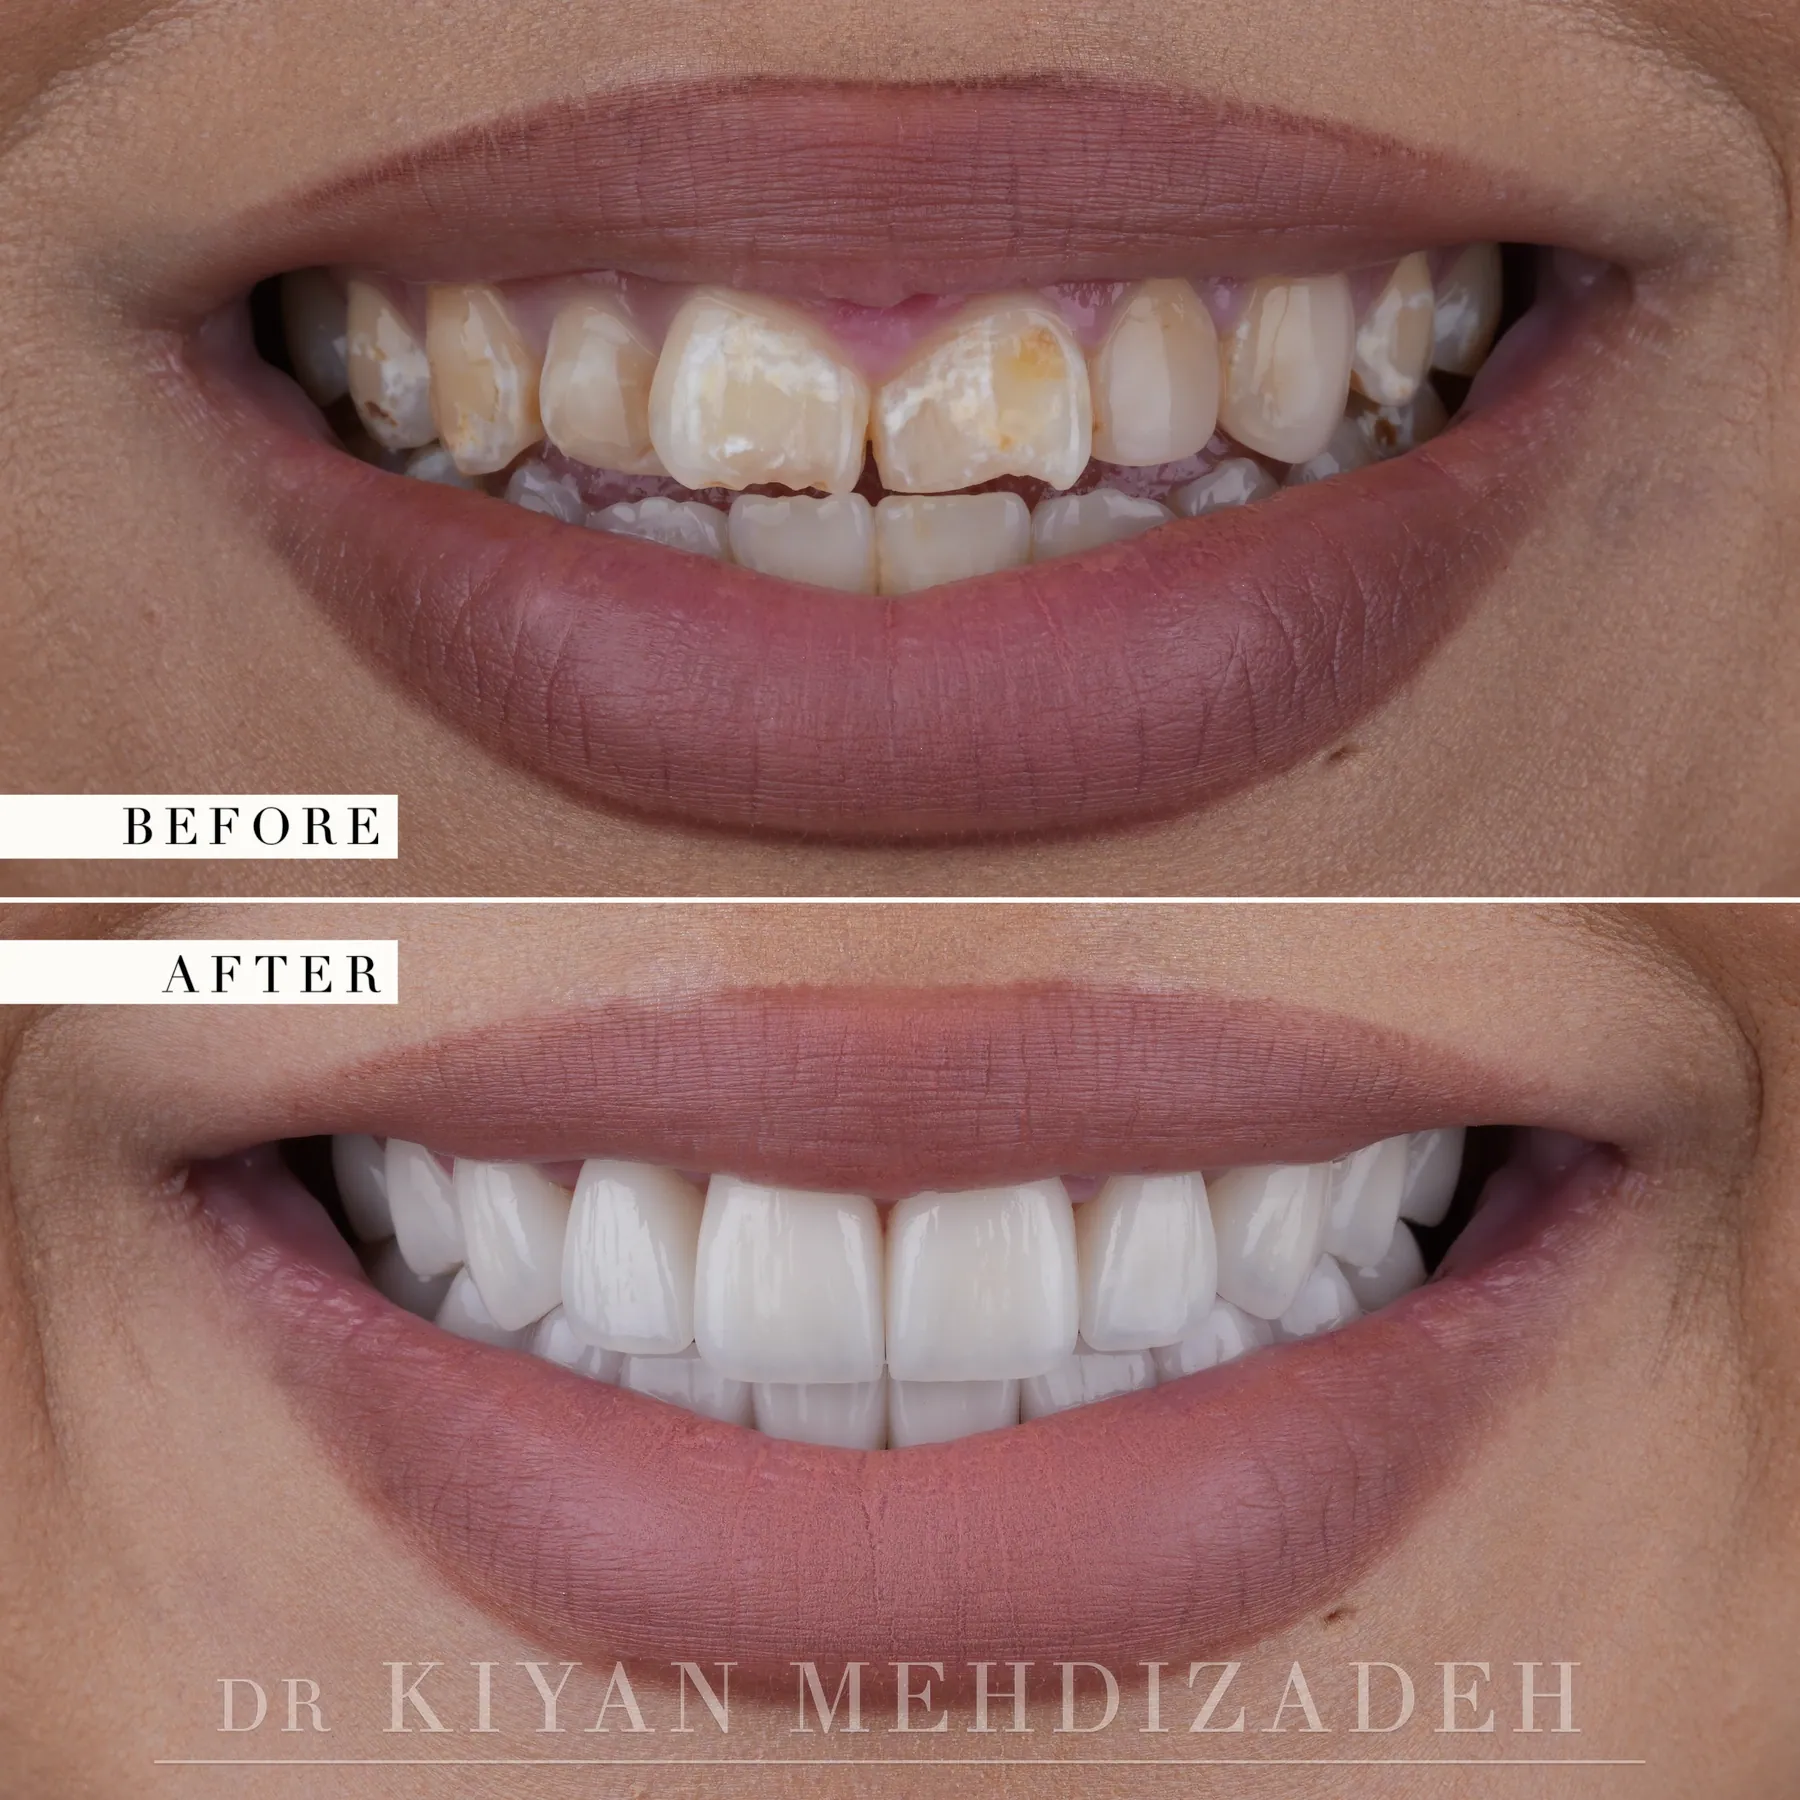

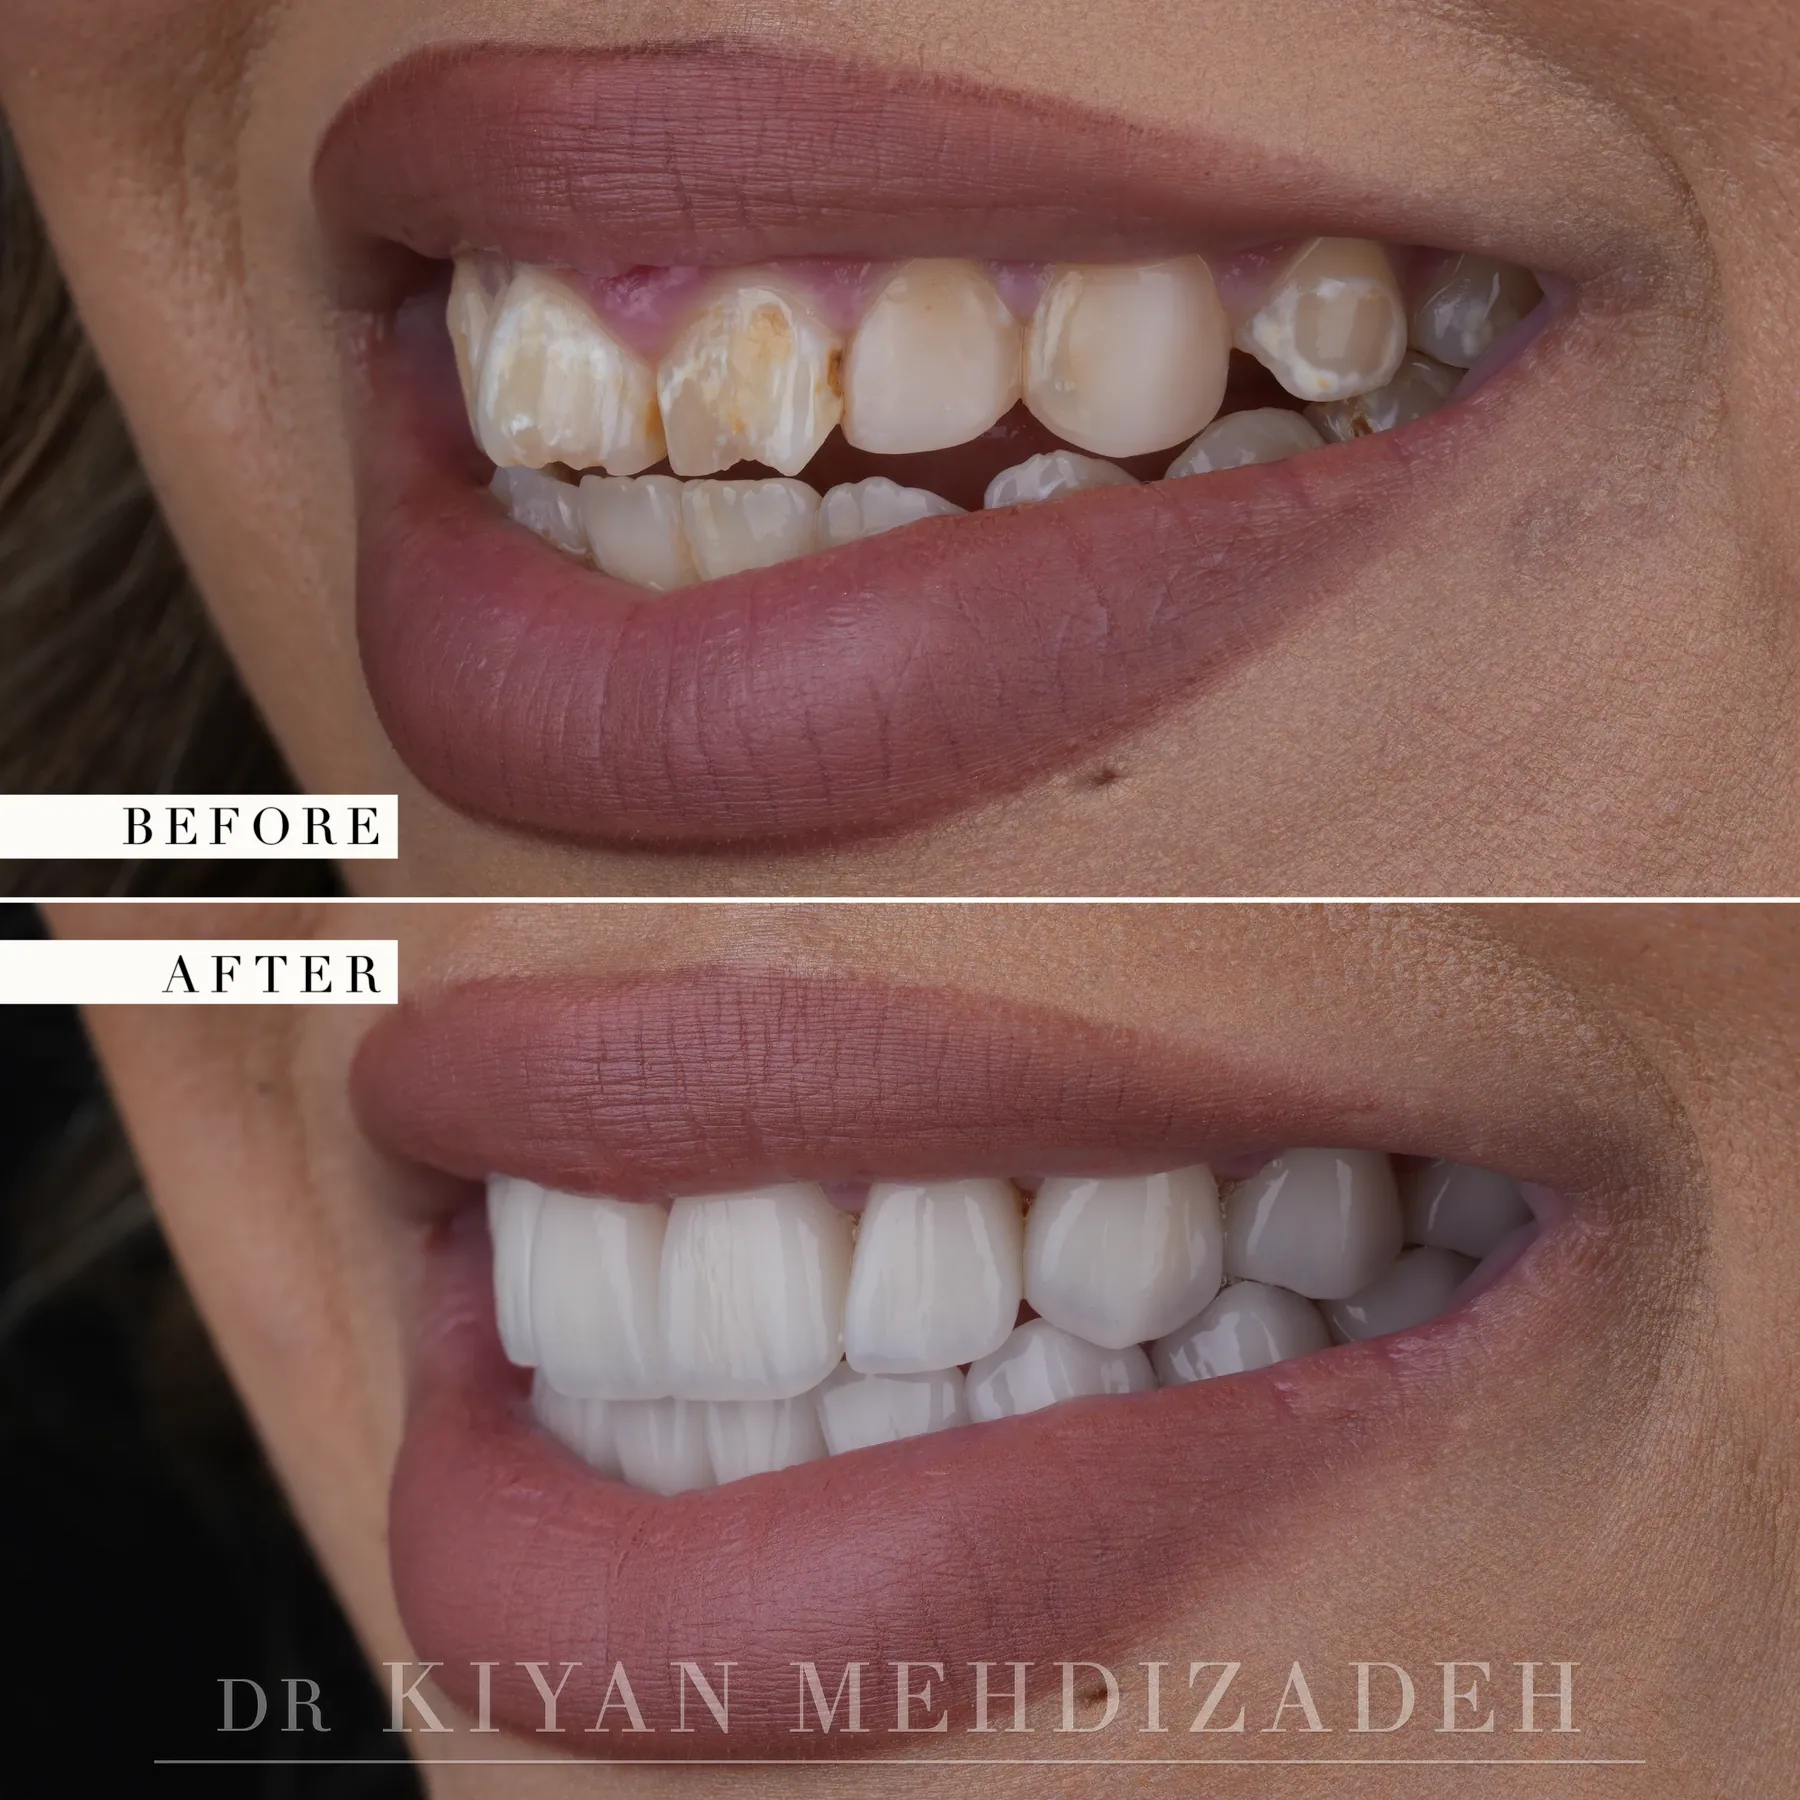
White marks left behind by braces?
Demineralization from braces leaves chalky white patches that bonding covers badly and briefly. If bonding has already been tried and failed, that is the normal outcome, not bad luck. Send us a photo and we will tell you what it would take.
- A call within two hours during office hours.
- A written cost from us, before you commit to anything.
- No obligation. Many patients take weeks to decide. That is normal.
What this case cost
$502/month
144 payments at 9.99% APR, on approved credit.
Total: $42,000 for twenty porcelain veneers, ten upper and ten lower.
Ask about your case
Reviewed by our treatment coordination team. Call or text (310) 770-3335 if you would rather speak now.
Request received
A treatment coordinator will call you within two hours during office hours (Monday to Friday, 9 to 4).
To talk now, call (310) 770-3335.
Treatment Plan by Dr. Mehdizadeh
- Complete removal of all existing failed composite bonding
- Excavation of decay from demineralized areas using minimally invasive techniques
- Upper and lower porcelain veneers to restore structure and aesthetics
- Restoration of proper tooth length and youthful proportions
- Natural surface texture with perikymata ridges for flat, lifelike appearance
What Is Demineralization from Braces and Why Does Bonding Fail to Fix It?
This patient came to us with the white spots and brown discoloration of demineralization, which occurs when acid-producing bacteria collect around bracket edges during treatment with metal braces. The problem was not just cosmetic. Demineralization is the first stage of tooth decay, and her teeth were actively deteriorating beneath the surface. Demineralization affects 50–70% of orthodontic patients to some degree, making it one of the most common complications of fixed bracket treatment.
She had already attempted to address the damage with dental bonding at another practice. As is common with composite bonding on demineralized teeth, the results were temporary at best. The composite resin had discolored within 2–3 years, turning yellow and gray where it met the natural tooth structure. Worse, it had begun to chip and crack, creating an uneven, patchy appearance that drew more attention to the problem than the original damage. She needed a lasting solution rather than another temporary repair.
“Bonding is a temporary fix. She needed a permanent solution.”
Why Dental Bonding Fails on Demineralized Teeth
Dental bonding has its place in cosmetic dentistry, but it does not hold up on significant demineralization. The composite resin used in bonding is inherently porous: it absorbs stains from coffee, tea, wine, and everyday foods at a rate that accelerates over time. Composite is also softer than natural enamel, measuring approximately 1–2 GPa on the hardness scale compared to enamel’s 3–5 GPa, meaning it wears differently and chips under normal biting forces.
The failure rate compounds when bonding sits on demineralized enamel. Healthy enamel provides a strong, predictable bond surface for composite resin. Demineralized enamel is weak, porous, and structurally compromised, resulting in bond strengths that are 30–50% lower than bonding to healthy tooth structure. This is why bonding on demineralized teeth fails faster, chips sooner, and develops marginal staining more quickly than bonding on intact enamel.
The Demineralization Problem
Demineralization creates both cosmetic and structural concerns. The white spots and brown discoloration are visible signs of enamel mineral loss. Beneath the surface, the tooth structure has weakened and is susceptible to cavities. Composite bonding masks the appearance temporarily but does not address the underlying decay, and fails prematurely due to poor adhesion to compromised enamel.
How We Treated the Demineralization and Decay
We began by removing all the existing composite bonding. That showed the full extent of the damage: acid had dissolved the enamel around the bracket sites, and early cavities had begun to form in several teeth. We treated the decay before any cosmetic work, removing all of it with minimally invasive techniques to preserve as much healthy tooth structure as possible, and stabilized the teeth with appropriate restorative materials.
With the foundation secure, Dr. Mehdizadeh designed upper and lower porcelain veneers to restore both the health and the appearance of her smile. The treatment addressed several issues simultaneously:
- Complete coverage of all demineralized and structurally compromised areas with protective porcelain
- Restoration of proper tooth length lost to wear, chipping, and the demineralization process
- Harmonized color across all visible teeth, eliminating the patchy appearance of failed bonding
- Natural surface texture with proper light reflection to avoid the bulky, artificial look
- Strengthened structural integrity through full-coverage bonding to healthy dentin
Why Surface Texture Matters in Porcelain Veneer Design
One of the most overlooked aspects of veneer design is surface texture. Natural teeth are not perfectly smooth. They have subtle vertical ridges called perikymata, horizontal developmental lines, and micro-texture that catches and reflects light in specific ways. When veneers lack this texture, they appear rounded, bulky, and obviously artificial regardless of how good the color match is.
Our ceramist builds surface characterization into every veneer. The result is teeth that appear flat and natural rather than rounded and fake. Light interacts with them the way it would with healthy natural enamel, creating a smile that looks authentic.
The Result After 4 Weeks of Treatment
Treatment took four weeks from consultation to final bonding. We removed the decay, porcelain that is harder and more stain-resistant than natural enamel now protects the weakened enamel, and her smile is both healthy and beautiful. We restored the tooth proportions to youthful dimensions, with width-to-length ratios of approximately 75–80%, and the surface texture reflects light naturally.
Porcelain veneers resist the discoloration, chipping and marginal staining that composite bonding develops. Porcelain measures approximately 6–7 GPa on the hardness scale, comparable to natural enamel, and its non-porous surface resists food and beverage stains. With proper care, porcelain veneers typically last 15–20 years. For someone whose teeth were deteriorating, the veneers restored her dental health as well as her appearance.
“A smile that’s finally healthy—and finally hers.”
Frequently Asked Questions About Demineralization, Bonding Failure, and Porcelain Veneers
What causes demineralization from braces?
Demineralization occurs when plaque accumulates around orthodontic brackets and brushing and flossing do not adequately remove it. The bacteria in plaque produce lactic acid that dissolves the mineral content of tooth enamel, creating characteristic white spots and weakened areas. Demineralization affects 50–70% of orthodontic patients. Once the braces come off, these damaged areas become visible and can progress to cavities if not treated. The damage is most common around the gum line and bracket margins where plaque is hardest to remove.
Why does dental bonding fail on demineralized teeth?
Dental bonding uses composite resin, which is porous and softer than natural enamel (1–2 GPa versus enamel’s 3–5 GPa). It absorbs stains and discolors over time, particularly at the margins where it meets the tooth. When bonding goes over demineralized enamel, the bond strength is 30–50% lower than on healthy enamel because the compromised surface cannot hold the adhesive properly. This causes faster failure, more chipping, and accelerated marginal staining. Bonding on demineralized teeth typically lasts only 2–4 years before needing replacement.
Can demineralization from braces be reversed without veneers?
Remineralization treatments such as prescription fluoride, MI Paste (casein phosphopeptide-amorphous calcium phosphate), or resin infiltration products like Icon can sometimes improve early demineralization limited to white spots without actual cavitation. However, once damage progresses to visible brown discoloration, structural weakness, or actual cavity formation, the tooth typically needs restorative treatment with porcelain veneers, both to protect it and to restore its appearance.
Why do the porcelain veneers look natural rather than bulky or fake?
Natural-looking veneers require careful attention to surface texture, not just color and shape. Our ceramist creates subtle perikymata ridges, developmental lines, and micro-surface characterization that mimic natural enamel. This allows light to reflect off the teeth naturally, producing a flat, lifelike appearance rather than the rounded, bulky look that makes veneers obviously artificial.
How much do porcelain veneers for demineralization correction cost?
This case was $42,000, covering twenty porcelain veneers, ten upper and ten lower. $502/month: 144 payments at 9.99% APR, on approved credit.
How long does the demineralization correction process take?
This case took 4 weeks. The process typically requires 3 appointments: decay removal and tooth preparation with temporary veneer placement, an optional ceramist try-in to verify shade and texture, and final bonding of the porcelain veneers. Most of that time the veneers are in our laboratory, where our ceramist hand-layers each one to achieve proper surface characterization and natural appearance.
How long do porcelain veneers last compared to composite bonding?
Composite bonding on demineralized teeth typically lasts 2–4 years before needing replacement due to staining, chipping, and marginal failure. High-quality porcelain veneers last 15–20 years or longer with proper care. Porcelain measures approximately 6–7 GPa on the hardness scale (comparable to natural enamel), resists staining, and maintains its appearance over time. For patients with significant demineralization, veneers represent a far more cost-effective long-term investment despite the higher upfront cost.
Are there alternatives to porcelain veneers for fixing demineralization?
Alternatives depend on severity. For mild white spots only, resin infiltration (Icon) or microabrasion may suffice. For moderate damage, new composite bonding provides a lower-cost option but with a 2–4 year lifespan on demineralized enamel. For severe demineralization with decay, porcelain crowns offer maximum coverage but require more tooth reduction than veneers. Porcelain veneers represent the best balance of protection, longevity, and minimal preparation for most demineralization cases involving both cosmetic and structural concerns.
Will demineralization continue under porcelain veneers?
When properly placed, porcelain veneers seal and protect the underlying tooth structure from further acid attack. The non-porous porcelain surface prevents bacterial adhesion, and the bonded margins create a closed seal. However, maintaining excellent oral hygiene along the gum line remains essential, as decay can still occur at the margin between the veneer and the natural tooth root if plaque accumulates. We recommend professional cleanings every 6 months.
Can porcelain veneers fix both the decay and cosmetic damage at the same time?
Yes. The treatment sequence addresses health first, then aesthetics. We remove all active decay and stabilize the teeth with appropriate restorative materials before any cosmetic work begins. The porcelain veneers then serve a dual purpose: they protect the restored tooth structure from further damage while simultaneously creating a natural, beautiful appearance. This combined restorative and cosmetic approach is one of the primary advantages of veneers for demineralization cases.
